Key Points
- HFrEF is generally LVEF 40% or lower in the current AHA/ACC/HFSA framework.
- Foundational therapy consists of ARNI or other RAS inhibition, evidence-based beta blocker, MRA, and SGLT2 inhibitor.
- Start the four classes early at tolerated doses instead of waiting to fully titrate each drug sequentially.
- SGLT2 inhibitors reduce HF events regardless of diabetes status.
- Loop diuretics treat congestion but do not replace mortality-reducing GDMT.
- Continue HFrEF therapy when EF improves unless a specific contraindication develops.
- Monitor potassium, creatinine, blood pressure, heart rate, and volume status during initiation and titration.
- Refer early for advanced-HF evaluation when recurrent decompensation or intolerance suggests progression.
Algorithm
- Confirm HFrEF by echocardiography and evaluate ischemic, valvular, rhythm, toxic, genetic, and systemic causes.
- Assess congestion, blood pressure, heart rate, renal function, potassium, iron status, and current medications.
- Initiate or optimize an ARNI or alternative RAS inhibitor, evidence-based beta blocker, MRA, and SGLT2 inhibitor as tolerated.
- Use loop diuretic therapy to achieve and maintain euvolemia.
- Recheck laboratory values and symptoms after each meaningful medication change and titrate toward evidence-based doses when feasible.
- Assess indications for hydralazine-isosorbide dinitrate, ivabradine, IV iron, anticoagulation for AF, or other adjuncts.
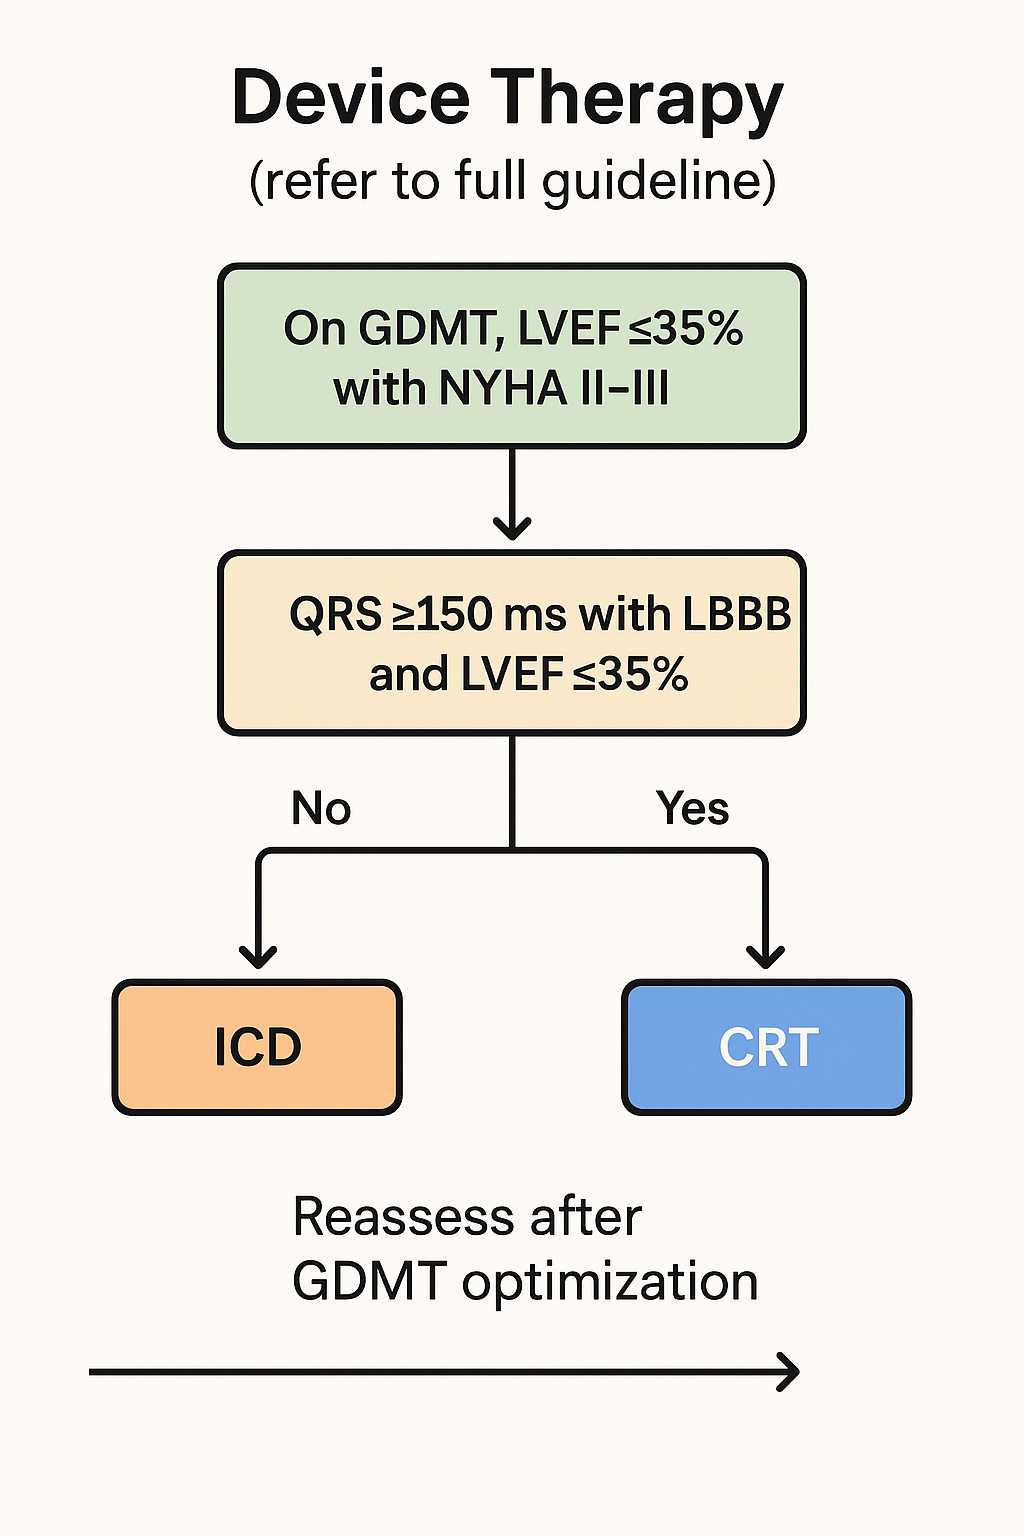
- Reassess EF after adequate GDMT when device therapy may be indicated and evaluate ICD or CRT criteria.
- Refer to an advanced HF team for recurrent admissions, persistent severe symptoms, shock, inotrope dependence, or progressive end-organ dysfunction.
Clinical Synopsis & Reasoning
HFrEF is a clinical syndrome of symptoms and signs caused by structural or functional cardiac disease with reduced left ventricular systolic function. Typical symptoms include exertional dyspnea, orthopnea, paroxysmal nocturnal dyspnea, edema, fatigue, and exercise intolerance. Evaluation should confirm LVEF, establish etiology, quantify congestion, identify reversible contributors, and define comorbidities that change treatment. Ischemic heart disease, prior myocardial infarction, hypertension, valvular disease, toxic exposures, myocarditis, genetic cardiomyopathy, tachyarrhythmia, and endocrine disease are important causes. A transthoracic echocardiogram is central to diagnosis and should document EF, ventricular dimensions, RV function, valve disease, and filling-pressure clues. BNP or NT-proBNP supports diagnosis when symptoms are nonspecific and has prognostic value, but levels are influenced by age, renal function, obesity, and atrial fibrillation. Evaluate iron status, renal function, potassium, blood pressure, diabetes, rhythm, and coronary disease. Patients whose EF improves above 40% after treatment are classified as HF with improved EF and should generally continue HFrEF therapy because withdrawal can lead to relapse. Distinguish chronic stable HFrEF from acute decompensation, because some medications can be initiated or continued in the hospital but hemodynamic instability, shock, severe AKI, or hyperkalemia may require temporary adjustment.
Treatment Strategy & Disposition
The four foundational HFrEF therapies should be started at low doses and brought on board early rather than waiting months to maximize one class before beginning the next. Sacubitril-valsartan is the preferred renin-angiotensin system inhibitor for symptomatic chronic HFrEF when tolerated; ACE inhibitors or ARBs remain alternatives when ARNI use is not feasible. Use an evidence-based beta blocker, specifically carvedilol, metoprolol succinate, or bisoprolol. Add a mineralocorticoid receptor antagonist such as spironolactone or eplerenone when renal function and potassium permit. Add an SGLT2 inhibitor such as dapagliflozin or empagliflozin regardless of diabetes status. Loop diuretics relieve congestion and should be titrated to maintain euvolemia, but they are not a substitute for disease-modifying therapy. Consider hydralazine-isosorbide dinitrate in self-identified Black patients with persistent symptomatic HFrEF despite optimal therapy and in patients unable to use renin-angiotensin inhibition. Ivabradine, digoxin, vericiguat, iron replacement, CRT, ICD therapy, revascularization, and advanced heart-failure therapies apply to selected patients. Titrate with close monitoring of blood pressure, heart rate, renal function, potassium, symptoms, and volume status. Refer patients with persistent NYHA III to IV symptoms, recurrent admissions, escalating diuretic need, inotrope dependence, progressive renal or hepatic dysfunction, or intolerance of foundational therapy to an advanced HF team.
Epidemiology / Risk Factors
- Ischemic heart disease and hypertension are major causes of HFrEF, but nonischemic and genetic cardiomyopathies are increasingly recognized.
- Diabetes, CKD, AF, obesity, sleep apnea, and iron deficiency commonly coexist and influence outcomes.
- Repeated HF hospitalization is a marker of disease progression and high short-term risk.
- Patients with improved EF remain biologically at risk for relapse despite apparent recovery.
- Access to and persistence with GDMT are major determinants of population-level outcomes.
Investigations
| Test | Role / Rationale | Typical Findings | Notes |
|---|---|---|---|
| Transthoracic echocardiogram | Confirms EF and structural disease | LVEF 40% or lower with variable chamber and valve findings | Repeat when clinical status changes or after GDMT when device decisions depend on EF |
| BNP or NT-proBNP | Supports diagnosis and prognosis | Elevated with increased wall stress | Interpret with age, obesity, CKD, and AF |
| BMP | Monitors creatinine, sodium, potassium, and bicarbonate | Hyponatremia, renal dysfunction, potassium abnormalities | Essential during GDMT titration and diuresis |
| CBC and iron studies | Detects anemia and iron deficiency | Low hemoglobin, ferritin, or transferrin saturation | Iron deficiency can impair function even without severe anemia |
| ECG | Identifies rhythm, QRS duration, prior infarction, and conduction disease | AF, LBBB, Q waves, or other abnormalities | QRS morphology helps determine CRT eligibility |
| Ischemic evaluation | Assesses coronary disease as cause or treatment target | Obstructive CAD or ischemia | Method depends on symptoms, pretest probability, and revascularization candidacy |
| Cardiac MRI | Characterizes myocardium and nonischemic etiologies | Scar, inflammation, infiltrative pattern | Useful when etiology remains unclear or infiltrative disease is suspected |
Core GDMT Components
| Class | Examples | Key Monitoring |
|---|---|---|
| ARNI or ACE inhibitor/ARB | Sacubitril-valsartan preferred when tolerated; ACE inhibitor or ARB if ARNI not feasible | Blood pressure, potassium, creatinine, angioedema history |
| Evidence-based beta blocker | Carvedilol, metoprolol succinate, bisoprolol | Heart rate, blood pressure, congestion, conduction disease |
| Mineralocorticoid receptor antagonist | Spironolactone, eplerenone | Potassium and kidney function |
| SGLT2 inhibitor | Dapagliflozin, empagliflozin | Volume status, renal function, genital infection, ketoacidosis risk |
| Loop diuretic for congestion | Furosemide, torsemide, bumetanide | Weight, symptoms, electrolytes, kidney function |
| Selected adjuncts | Hydralazine-isosorbide dinitrate, ivabradine, IV iron, device therapy | Eligibility is phenotype specific and should not delay foundational GDMT |
Pharmacology
| Medication | Mechanism | Onset | Role in Therapy | Limitations |
|---|---|---|---|---|
| Sacubitril-valsartan | Neprilysin inhibition plus angiotensin receptor blockade | Days to weeks | Preferred RAS-pathway therapy for many symptomatic HFrEF patients | Hypotension, hyperkalemia, renal effects; avoid with prior angioedema and observe ACE inhibitor washout |
| Carvedilol, metoprolol succinate, or bisoprolol | Evidence-based beta blockade | Weeks to months | Reduces mortality and hospitalization | Start when reasonably euvolemic and stable; bradycardia or hypotension |
| Spironolactone or eplerenone | Mineralocorticoid receptor blockade | Days to weeks | Reduces mortality and hospitalization in eligible HFrEF | Hyperkalemia and renal dysfunction; gynecomastia with spironolactone |
| Dapagliflozin or empagliflozin | SGLT2 inhibition with cardiorenal effects | Days to weeks | Reduces HF hospitalization and cardiovascular death regardless of diabetes | Genital infection, volume depletion, rare ketoacidosis |
| Loop diuretic | Inhibits sodium reabsorption in loop of Henle | Hours | Relieves congestion | Electrolyte loss, renal dysfunction, ototoxicity at high doses |
| Hydralazine plus isosorbide dinitrate | Arterial and venous vasodilation | Hours | Selected persistent symptomatic HFrEF or inability to use RAS inhibition | Headache, hypotension, adherence burden |
Prognosis / Complications
- The four foundational therapies substantially reduce death and HF hospitalization when tolerated and continued.
- Persistent congestion at discharge predicts early readmission and mortality.
- Improving EF generally improves prognosis but does not eliminate relapse risk.
- Sudden arrhythmic death and progressive pump failure remain major causes of mortality in advanced HFrEF.
- Early advanced-HF referral can preserve options for LVAD or transplantation before irreversible end-organ dysfunction develops.
Patient Education / Counseling
- Explain the purpose of each foundational medication, including drugs that are prescribed for heart failure even when blood pressure or diabetes are not the primary problem.
- Teach daily symptom and weight awareness and provide a clinician-specific plan for worsening edema or dyspnea.
- Avoid NSAIDs unless specifically advised and review sodium, alcohol, smoking, and fluid guidance individually.
- Seek urgent care for severe breathlessness at rest, syncope, chest pain, rapidly progressive swelling, or confusion.
- Keep laboratory follow-up after medication changes because potassium and kidney function can change before symptoms appear.
Notes
The practical goal is rapid, safe implementation of all four foundational therapies. Waiting several months to maximize one medication before starting the others delays benefit because each class works through a different pathway and can improve outcomes within weeks. Titration should be individualized rather than abandoned when low blood pressure or kidney dysfunction appears. First determine whether the patient is congested, dehydrated, over-diuresed, or taking unnecessary blood-pressure-lowering medication. Many patients tolerate lower doses of all four classes better than a high dose of only one or two. Continue surveillance after EF improves because withdrawal of therapy can lead to recurrent systolic dysfunction.
Exhibits
References
- 2022 AHA/ACC/HFSA Guideline for the Management of Heart Failure — Link
Turn pharmacology review into vignette practice.
Most students do not plateau because they refuse to study. They plateau because their review does not show the exact reasoning error behind repeated misses. MDSteps turns topic review into targeted blocks, explanations, flashcards, and readiness signals.
- Full access to 1,100+ medical reference articles linked directly to relevant QBank concepts
- 16,000+ USMLE-style questions across Step 1, Step 2 CK, and Step 3
- Depth-on-Demand™ explanations that isolate the pivot clue, distractor trap, and decision point
- CCS cases with live vitals, order timing, reassessment, and after-action feedback